
 ,
Carmel Gloria Abatti,
Sèssédè Rineste Verane Sagbohan,
Sahossi Gracias,
Cyrille Dossou,
Jean de Dieu Yelouassi,
David Mawu-Kolo Bokodaho,
Djidjoho Joël Arnaud Sonou,
Léopold Houétondji Codjo
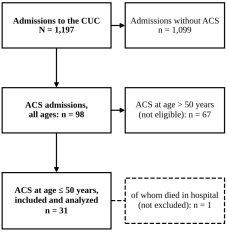
Acute coronary syndrome (ACS) in young adults is uncommon, but it is increasingly reported, including in sub-Saharan Africa. The aim of this study was to describe the epidemiological, diagnostic, therapeutic and in-hospital outcome features of ACS in young adults at the University Clinic of Cardiology (CUC) of the Hubert Koutoukou Maga National University Hospital Center (CNHU-HKM) in Cotonou, Benin. We conducted a single-center, cross-sectional, descriptive study with prospective data collection from 1 January 2020 to 31 August 2022. ACS was diagnosed according to the Fourth Universal Definition of Myocardial Infarction and the European Society of Cardiology guidelines. All patients aged 50 years or younger who were admitted to the CUC with ACS and gave informed consent were included and followed until discharge or death. Among 98 ACS admissions of all ages, 31 (31.6%) concerned patients aged 50 years or younger, who represented 2.6% of the 1,197 admissions. Among the 31 patients included, the mean age was 40.9 ± 7.7 years, with a marked male predominance (87.1%). Pre-event cardiovascular risk, estimated descriptively with the SCORE2 charts, was low in 48.4% of patients. The mean time from symptom onset to admission was 37.8 ± 41.3 hours, and 58.1% of patients were admitted more than 12 hours after onset. ST-elevation ACS accounted for 71.0% of cases. A high probability of atherosclerotic origin according to an exploratory, non-validated score was found in 96.8% of patients; it could not be confirmed angiographically in most of them. All patients except the one who died received the BASIC regimen (beta-blockers, antiplatelet agents, statins, renin–angiotensin system inhibitors and control of cardiovascular risk factors). Thrombolysis was indicated in nine patients, performed in seven (22.6%) and successful in six. Five patients (16.1%) underwent coronary angiography, which showed significant stenoses in three of them; these three patients received drug-eluting stents. At least one in-hospital complication occurred in 41.9% of patients, and in-hospital mortality was 3.2%. In this single-center series, ACS in patients aged 50 years or younger accounted for about one third of ACS admissions. Most of the risk factors observed were modifiable. These descriptive findings, limited by the small sample and the lack of systematic coronary angiography, support the strengthening of preventive measures and of access to reperfusion.
| Published in | Cardiology and Cardiovascular Research (Volume 10, Issue 4) |
| DOI | 10.11648/j.ccr.20261004.13 |
| Page(s) | 118-129 |
| Creative Commons |
This is an Open Access article, distributed under the terms of the Creative Commons Attribution 4.0 International License (http://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, distribution and reproduction in any medium or format, provided the original work is properly cited. |
| Copyright |
Copyright © The Author(s), 2026. Published by Science Publishing Group |
Acute Coronary Syndrome, Young Adults, Cardiovascular Risk Factors, Thrombolysis, Benin
Item | Points |
|---|---|
History of hypertension | 3 |
History of diabetes | 3 |
Current smoking | 3 |
Atherogenic dyslipidemia | 3 |
Family history of sudden death in a first-degree relative | 1 |
Family history of MI in a first-degree relative | 2 |
CIMT between 0.7 and 1 mm | 2 |
CIMT > 1 mm | 4 |
Reduced ABI | 4 |
History of VTE | −2 |
Total score | Sum of points |
Risk factor | n | % |
|---|---|---|
Hypertension | 10 | 32.26 |
Diabetes | 5 | 16.13 |
Smoking | 5 | 16.13 |
Dyslipidemia | 30 | 96.77 |
LDL hypercholesterolemia | 25 | 80.65 |
Low HDL cholesterol | 10 | 32.26 |
Hypertriglyceridemia | 10 | 32.26 |
Overweight | 16 | 51.61 |
General obesity | 7 | 22.58 |
Abdominal obesity | 13 | 41.94 |
Personal history of MI | 3 | 9.68 |
Excessive alcohol consumption | 2 | 6.45 |
Family history of premature stroke | 0 | 0.00 |
Family history of MI | 1 | 3.23 |
Family history of sudden death | 1 | 3.23 |
Family history of hypertension | 14 | 45.16 |
Family history of diabetes | 9 | 29.03 |
Characteristic | n | % |
|---|---|---|
Type of ACS | ||
STE-ACS | 22 | 70.97 |
NSTE-ACS, troponin-positive | 7 | 22.58 |
NSTE-ACS, troponin-negative | 2 | 6.45 |
Electrocardiographic territory | ||
Anteroseptal | 7 | 22.58 |
Apical | 5 | 16.13 |
High lateral | 4 | 12.90 |
Low lateral | 7 | 22.58 |
Extensive anterior | 10 | 32.26 |
Inferior | 23 | 74.19 |
Basal | 9 | 29.03 |
Right ventricle | 10 | 32.26 |
Patient (age, years) | Angiographic findings | Treatment |
|---|---|---|
1 (40) | Three-vessel disease. Significant stenoses: second diagonal, Cx, RCA. Non-significant lesion: LAD. | Two DES (RCA, Cx) |
2 (49) | Three-vessel disease. Significant stenoses: LAD, first and second diagonals, RCA, RVP. Chronic occlusion of the Cx. Non-significant lesion: left main. | Two DES (RCA); primary-prevention ICD |
3 (34) | Two-vessel disease. Non-significant lesions: LAD, RCA. | Medical treatment |
4 (49) | Three-vessel disease. Significant stenoses: distal LAD, second diagonal, distal RCA. Non-significant lesion: first marginal. | Two DES (distal RCA, second diagonal) |
5 (49) | Three-vessel disease. Non-significant lesions: LAD, Cx, RCA. | Medical treatment |
Complication | n | % |
|---|---|---|
Arrhythmias | 8 | 61.54 |
Conduction disorders | 4 | 30.77 |
Left ventricular failure | 4 | 30.77 |
Pericarditis | 2 | 15.38 |
Cardiogenic shock | 1 | 7.69 |
Left ventricular thrombus | 1 | 7.69 |
Death | 1 | 7.69 |
ABI | Ankle-brachial Index |
ACS | Acute Coronary Syndrome |
AF | Atrial Fibrillation |
AV | Atrioventricular |
BMI | Body Mass Index |
CI | Confidence Interval |
CIMT | Carotid Intima-media Thickness |
CNHU-HKM | Hubert Koutoukou Maga National University Hospital Center |
CUC | University Clinic of Cardiology |
DES | Drug-eluting Stent |
ECG | Electrocardiogram |
ESC | European Society of Cardiology |
HDL | High-density Lipoprotein |
hs-cTnI | High-sensitivity Cardiac Troponin I |
ICD | Implantable Cardioverter-defibrillator |
LDL | Low-density Lipoprotein |
LV | Left Ventricular |
LVEF | Left Ventricular Ejection Fraction |
LVH | Left Ventricular Hypertrophy |
MI | Myocardial Infarction |
NSTE-ACS | Non–ST-elevation Acute Coronary Syndrome |
NSTEMI | Non–ST-elevation Myocardial Infarction |
PAC | Premature Atrial Contraction |
PCI | Percutaneous Coronary Intervention |
PROCAM | Prospective Cardiovascular Münster |
PVC | Premature Ventricular Contraction |
SCORE2 | Systematic COronary Risk Evaluation 2 |
SD | Standard Deviation |
STE-ACS | ST-elevation Acute Coronary Syndrome |
STEMI | ST-elevation Myocardial Infarction |
URL | Upper Reference Limit |
VT | Ventricular Tachycardia |
VTE | Venous Thromboembolism |
WHO | World Health Organization |
| [1] | Tunstall-Pedoe, H., Kuulasmaa, K., et al. Myocardial infarction and coronary deaths in the World Health Organization MONICA Project. Registration procedures, event rates, and case-fatality rates in 38 populations from 21 countries in four continents. Circulation. 1994, 90(1), 583-612. |
| [2] | Dujardin, J. J., Cambou, J. P. Épidémiologie de l'infarctus du myocarde [Epidemiology of myocardial infarction]. EMC-Cardiologie Angéiologie. 2005, 2, 375-387. (in French) |
| [3] |
Tea, V., Danchin, N., Puymirat, E. Infarctus du myocarde du sujet jeune: spécificités épidémiologiques et facteurs de risque [Myocardial infarction in young subjects: epidemiological specificities and risk factors]. Presse Med. 2019, 48(12), 1383-1386.
https://doi.org/10.1016/j.lpm.2019.06.001 (in French) |
| [4] | Collet, J. P., Ripoll, L., Choussat, R., Lison, L., Montalescot, G. La maladie athérothrombotique coronaire du sujet jeune: état des lieux [Coronary atherothrombotic disease in young subjects: current situation]. Sang Thrombose Vaisseaux. 2000, 12, 218-225. (in French) |
| [5] | Grenier, O., Cambou, J. P., Ferrières, J., Thomas, D., Amelineau, E., Cantet, C., et al. Caractéristiques initiales et prise en charge thérapeutique de sujets jeunes (âge inférieur à 45 ans) hospitalisés pour syndrome coronarien aigu: résultats des études françaises PREVENIR 1 et PREVENIR 2 [Baseline characteristics and therapeutic management of young subjects (younger than 45 years) hospitalized for acute coronary syndrome: results of the French PREVENIR 1 and PREVENIR 2 studies]. Ann Cardiol Angeiol (Paris). 2002, 51(1), 15-19. (in French) |
| [6] | Pasricha, A., Batchelor, W. When young hearts are broken: profiles of premature myocardial infarction. Am Heart J. 2002, 143(1), 4-6. |
| [7] | Marques-Vidal, P., Cambou, J. P., Ferrières, J., Thomas, D., Grenier, O., Cantet, C., et al. Distribution et prise en charge des facteurs de risque cardiovasculaires chez des patients coronariens: étude PREVENIR [Distribution and management of cardiovascular risk factors in coronary patients: the PREVENIR study]. Arch Mal Cœur Vaiss. 2001, 94(7), 673-680. (in French) |
| [8] | Dakpo, M. Particularités de l'infarctus du myocarde chez le sujet jeune à l'unité de soins, d'enseignement et de recherche en cardiologie du CNHU-HKM de Cotonou [Particularities of myocardial infarction in young subjects at the cardiology care, teaching and research unit of the CNHU-HKM, Cotonou]. Specialized Studies Diploma (DES) Thesis in Cardiovascular Diseases, University of Abomey-Calavi, Cotonou, Benin, 2017, 90 p. (in French) |
| [9] | Thygesen, K., Alpert, J. S., Jaffe, A. S., Chaitman, B. R., Bax, J. J., Morrow, D. A., White, H. D. Fourth universal definition of myocardial infarction (2018). Eur Heart J. 2019, 40(3), 237-269. |
| [10] | Ibanez, B., James, S., Agewall, S., Antunes, M. J., Bucciarelli-Ducci, C., Bueno, H., et al. 2017 ESC Guidelines for the management of acute myocardial infarction in patients presenting with ST-segment elevation. Eur Heart J. 2018, 39(2), 119-177. |
| [11] | Collet, J. P., Thiele, H., Barbato, E., Barthélémy, O., Bauersachs, J., Bhatt, D. L., et al. 2020 ESC Guidelines for the management of acute coronary syndromes in patients presenting without persistent ST-segment elevation. Eur Heart J. 2021, 42(14), 1289-1367. |
| [12] | Byrne, R. A., Rossello, X., Coughlan, J. J., Barbato, E., Berry, C., Chieffo, A., et al. 2023 ESC Guidelines for the management of acute coronary syndromes. Eur Heart J. 2023, 44(38), 3720-3826. |
| [13] | Mach, F., Baigent, C., Catapano, A. L., Koskinas, K. C., et al. 2019 ESC/EAS Guidelines for the management of dyslipidaemias: lipid modification to reduce cardiovascular risk. Eur Heart J. 2020, 41(1), 111-188. |
| [14] | Visseren, F. L. J., Mach, F., Smulders, Y. M., Carballo, D., et al. 2021 ESC Guidelines on cardiovascular disease prevention in clinical practice. Eur Heart J. 2021, 42(34), 3227-3337. |
| [15] | SCORE2 working group and ESC Cardiovascular risk collaboration. SCORE2 risk prediction algorithms: new models to estimate 10-year risk of cardiovascular disease in Europe. Eur Heart J. 2021, 42(25), 2439-2454. |
| [16] | Lawton, J. S., Tamis-Holland, J. E., Bangalore, S., Bates, E. R., Beckie, T. M., Bischoff, J. M., et al. 2021 ACC/AHA/SCAI Guideline for Coronary Artery Revascularization: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Circulation. 2022, 145(3), e18-e114. |
| [17] | Peerwani, G., Hanif, B., Rahim, K. A., et al. Presentation, management, and early outcomes of young acute coronary syndrome patients: analysis of 23,560 South Asian patients from 2012 to 2021. BMC Cardiovasc Disord. 2024, 24, 378. |
| [18] | Coulibaly, S., Diall, I., Menta, I. Facteurs de risque et aspects cliniques de l'infarctus du myocarde chez les patients de moins de 40 ans au CHU du Point G [Risk factors and clinical aspects of myocardial infarction in patients younger than 40 years at the Point G University Hospital]. Mali Médical. 2014, 29(4), 35-38. (in French) |
| [19] | Yaméogo, N. V., Ndiaye, M. B., Mbaye, A., et al. Myocardial infarction in the young adult - Retrospective analysis of cases compile at the University Hospital of Dakar. Pan Afr Med J. 2010, 6, 21. |
| [20] | Sylla, I. S. I., Baldé, M. D., Béavogui, M., et al. Infarctus du myocarde des sujets de moins de 50 ans: aspects épidémiologiques, cliniques, paracliniques et pronostiques: à propos de 29 cas au service de cardiologie de l'Hôpital National Ignace Deen [Myocardial infarction in subjects younger than 50 years: epidemiological, clinical, paraclinical and prognostic aspects: 29 cases in the cardiology department of the Ignace Deen National Hospital]. Rev Int Sci Méd (RISM). 2017, 19(3), 196-199. (in French) |
| [21] | Matsis, K., Holley, A., Al-Sinan, A., Matsis, P., Larsen, P. D., Harding, S. A. Differing clinical characteristics between young and older patients presenting with myocardial infarction. Heart Lung Circ. 2017, 26(6), 566-571. |
| [22] | Shah, V., Jain, U. Clinical profile of acute myocardial infarction in young adults. Int J Med Sci Public Health. 2016, 5, 1709-1713. |
| [23] | Adoubi, K. A., Adoh, A. M., Konin, C., Ndjessan, J. J., et al. Aspects épidémiologiques, cliniques et pronostiques de l'infarctus du myocarde à l'Institut de Cardiologie d'Abidjan de 1999 à 2006 [Epidemiological, clinical and prognostic aspects of myocardial infarction at the Abidjan Institute of Cardiology from 1999 to 2006]. Cah Santé Publique. 2010, 9(1), 65-72. (in French) |
| [24] | Mboup, M. C., Diao, M., Dia, K., Fall, P. D. Acute coronary syndromes in Dakar: therapeutic, clinical and evolutionary aspects. Pan Afr Med J. 2014, 19, 126. |
| [25] | Mahdhaoui, A., Bouraoui, H., Majdoub, M. A., et al. Délais de prise en charge de l'IDM en phase aiguë: résultats d'une enquête dans la région de Sousse (Tunisie) [Delays in the management of acute myocardial infarction: results of a survey in the Sousse region (Tunisia)]. Ann Cardiol Angéiol. 2003, 52(1), 15-19. (in French) |
| [26] | Pitsavos, C., Panagiotakos, D. B., Antonoulas, A., et al. Epidemiology of acute coronary syndromes in a Mediterranean country; aims, design and baseline characteristics of the Greek study of acute coronary syndromes (GREECS). BMC Public Health. 2005, 5, 23. |
| [27] | De Lopagno, S. M. Syndrome coronarien aigu: analyse des délais de la prise en charge [Acute coronary syndrome: analysis of management delays]. Doctoral Thesis in Medicine, University of Geneva, Switzerland, 2004, No. 10397. (in French) |
| [28] |
Joussein-Remacle, S., Delarche, N., Bader, H., Lasserre, R., Estrade, G. Facteurs de risque de l'infarctus du myocarde du sujet jeune: registre prospectif sur un an [Risk factors for myocardial infarction in young subjects: a one-year prospective registry]. Ann Cardiol Angeiol. 2006, 55(4), 204-209.
https://doi.org/10.1016/j.ancard.2006.05.001 (in French) |
| [29] | Belle, L., Cayla, G., Cottin, Y., Coste, P., et al. French Registry on Acute ST-elevation and non-ST-elevation Myocardial Infarction 2015 (FAST-MI 2015). Design and baseline data. Arch Cardiovasc Dis. 2017. |
| [30] | Lamzarraf, S. L'infarctus du myocarde du sujet jeune [Myocardial infarction in young subjects]. Doctoral Thesis in Medicine, Cadi Ayyad University, Marrakech, Morocco, 2010, No. 66, 88 p. (in French) |
| [31] | Kassam, N., Ngunga, M., Varwani, M., et al. Acute coronary syndrome patterns in the young: risk factor profile and in-hospital outcomes in a tertiary referral hospital in Kenya. BMC Cardiovasc Disord. 2024, 24, 192. |
| [32] | Lorenz, M. W., Markus, H. S., Bots, M. L., Rosvall, M., Sitzer, M. Prediction of clinical cardiovascular events with carotid intima-media thickness: a systematic review and meta-analysis. Circulation. 2007, 115(4), 459-467. |
| [33] | Herinirina, N. F., Rajaonarison, L. H., Herijoelison, A. R., Ahmad, A. Thickness of carotid intima-media and cardiovascular risk factors. Pan Afr Med J. 2015, 21, 153. |
| [34] | Chambless, L. E., Heiss, G., Folsom, A. R., et al. Association of coronary heart disease incidence with carotid arterial wall thickness and major risk factors: the Atherosclerosis Risk in Communities (ARIC) Study, 1987-1993. Am J Epidemiol. 1997, 146(6), 483-494. |
| [35] | Kwon, T. G., Kim, K. H., Yoon, H. J., et al. The prognostic significance of carotid intima-media thickness in patients who underwent percutaneous coronary intervention. Korean Circ J. 2007, 37(3), 103-107. |
| [36] | Tropeano, A. I. Mise au point: épaisseur intima-média carotidienne: quelle plus-value dans l'évaluation du risque cardiovasculaire? [Update: carotid intima-media thickness: what added value in cardiovascular risk assessment?]. La Lettre du Cardiologue. 2010, 433, 18-21. (in French) |
| [37] | Zimmerman, F. H., Cameron, A., Fisher, L. D., Ng, G. Myocardial infarction in young adults: angiographic characterization, risk factors and prognosis (Coronary Artery Surgery Study Registry). J Am Coll Cardiol. 1995, 26, 654-661. |
| [38] | Adlam, D., Alfonso, F., Maas, A., Vrints, C. European Society of Cardiology, Acute Cardiovascular Care Association, SCAD Study Group: a position paper on spontaneous coronary artery dissection. Eur Heart J. 2018, 39(36), 3353-3368. |
| [39] |
N'Guetta, R., et al. Prévalence et caractéristiques des syndromes coronariens aigus dans une population d'Afrique subsaharienne [Prevalence and characteristics of acute coronary syndromes in a sub-Saharan African population]. Ann Cardiol Angeiol (Paris). 2016.
https://doi.org/10.1016/j.ancard.2016.01.001 (in French) |
| [40] | Shah, N., Kelly, A. M., Cox, N., Wong, C., Soon, K. Myocardial infarction in the "young": risk factors, presentation, management and prognosis. Heart Lung Circ. 2016, 25(10), 955-960. |
| [41] | Fournier, J. A., Cabezón, S., Cayuela, A., et al. Long-term prognosis of patients having acute myocardial infarction when ≤ 40 years of age. Am J Cardiol. 2004, 94(8), 989-992. |
APA Style
Moussa, R. K., Abatti, C. G., Sagbohan, S. R. V., Gracias, S., Dossou, C., et al. (2026). Acute Coronary Syndrome in Young Adults at a University Hospital in Cotonou, Benin: Epidemiological, Diagnostic, Therapeutic and Outcome Aspects. Cardiology and Cardiovascular Research, 10(4), 118-129. https://doi.org/10.11648/j.ccr.20261004.13
ACS Style
Moussa, R. K.; Abatti, C. G.; Sagbohan, S. R. V.; Gracias, S.; Dossou, C., et al. Acute Coronary Syndrome in Young Adults at a University Hospital in Cotonou, Benin: Epidemiological, Diagnostic, Therapeutic and Outcome Aspects. Cardiol. Cardiovasc. Res. 2026, 10(4), 118-129. doi: 10.11648/j.ccr.20261004.13
AMA Style
Moussa RK, Abatti CG, Sagbohan SRV, Gracias S, Dossou C, et al. Acute Coronary Syndrome in Young Adults at a University Hospital in Cotonou, Benin: Epidemiological, Diagnostic, Therapeutic and Outcome Aspects. Cardiol Cardiovasc Res. 2026;10(4):118-129. doi: 10.11648/j.ccr.20261004.13
@article{10.11648/j.ccr.20261004.13,
  author = {Rachad Kondo Moussa and Carmel Gloria Abatti and Sèssédè Rineste Verane Sagbohan and Sahossi Gracias and Cyrille Dossou and Jean de Dieu Yelouassi and Ghislaine Armelle Melo Teche and David Mawu-Kolo Bokodaho and Murielle Hounkponou and Djidjoho Joël Arnaud Sonou and Léopold Houétondji Codjo},
  title = {Acute Coronary Syndrome in Young Adults at a University Hospital in Cotonou, Benin: Epidemiological, Diagnostic, Therapeutic and Outcome Aspects},
  journal = {Cardiology and Cardiovascular Research},
  volume = {10},
  number = {4},
  pages = {118-129},
  doi = {10.11648/j.ccr.20261004.13},
  url = {https://doi.org/10.11648/j.ccr.20261004.13},
  eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.ccr.20261004.13},
  abstract = {Acute coronary syndrome (ACS) in young adults is uncommon, but it is increasingly reported, including in sub-Saharan Africa. The aim of this study was to describe the epidemiological, diagnostic, therapeutic and in-hospital outcome features of ACS in young adults at the University Clinic of Cardiology (CUC) of the Hubert Koutoukou Maga National University Hospital Center (CNHU-HKM) in Cotonou, Benin. We conducted a single-center, cross-sectional, descriptive study with prospective data collection from 1 January 2020 to 31 August 2022. ACS was diagnosed according to the Fourth Universal Definition of Myocardial Infarction and the European Society of Cardiology guidelines. All patients aged 50 years or younger who were admitted to the CUC with ACS and gave informed consent were included and followed until discharge or death. Among 98 ACS admissions of all ages, 31 (31.6%) concerned patients aged 50 years or younger, who represented 2.6% of the 1,197 admissions. Among the 31 patients included, the mean age was 40.9 ± 7.7 years, with a marked male predominance (87.1%). Pre-event cardiovascular risk, estimated descriptively with the SCORE2 charts, was low in 48.4% of patients. The mean time from symptom onset to admission was 37.8 ± 41.3 hours, and 58.1% of patients were admitted more than 12 hours after onset. ST-elevation ACS accounted for 71.0% of cases. A high probability of atherosclerotic origin according to an exploratory, non-validated score was found in 96.8% of patients; it could not be confirmed angiographically in most of them. All patients except the one who died received the BASIC regimen (beta-blockers, antiplatelet agents, statins, renin–angiotensin system inhibitors and control of cardiovascular risk factors). Thrombolysis was indicated in nine patients, performed in seven (22.6%) and successful in six. Five patients (16.1%) underwent coronary angiography, which showed significant stenoses in three of them; these three patients received drug-eluting stents. At least one in-hospital complication occurred in 41.9% of patients, and in-hospital mortality was 3.2%. In this single-center series, ACS in patients aged 50 years or younger accounted for about one third of ACS admissions. Most of the risk factors observed were modifiable. These descriptive findings, limited by the small sample and the lack of systematic coronary angiography, support the strengthening of preventive measures and of access to reperfusion.},
 year = {2026}
}
TY  - JOUR
T1  - Acute Coronary Syndrome in Young Adults at a University Hospital in Cotonou, Benin: Epidemiological, Diagnostic, Therapeutic and Outcome Aspects
AU  - Rachad Kondo Moussa
AU  - Carmel Gloria Abatti
AU  - Sèssédè Rineste Verane Sagbohan
AU  - Sahossi Gracias
AU  - Cyrille Dossou
AU  - Jean de Dieu Yelouassi
AU  - Ghislaine Armelle Melo Teche
AU  - David Mawu-Kolo Bokodaho
AU  - Murielle Hounkponou
AU  - Djidjoho Joël Arnaud Sonou
AU  - Léopold Houétondji Codjo
Y1  - 2026/11/16
PY  - 2026
N1  - https://doi.org/10.11648/j.ccr.20261004.13
DO  - 10.11648/j.ccr.20261004.13
T2  - Cardiology and Cardiovascular Research
JF  - Cardiology and Cardiovascular Research
JO  - Cardiology and Cardiovascular Research
SP  - 118
EP  - 129
PB  - Science Publishing Group
SN  - 2578-8914
UR  - https://doi.org/10.11648/j.ccr.20261004.13
AB  - Acute coronary syndrome (ACS) in young adults is uncommon, but it is increasingly reported, including in sub-Saharan Africa. The aim of this study was to describe the epidemiological, diagnostic, therapeutic and in-hospital outcome features of ACS in young adults at the University Clinic of Cardiology (CUC) of the Hubert Koutoukou Maga National University Hospital Center (CNHU-HKM) in Cotonou, Benin. We conducted a single-center, cross-sectional, descriptive study with prospective data collection from 1 January 2020 to 31 August 2022. ACS was diagnosed according to the Fourth Universal Definition of Myocardial Infarction and the European Society of Cardiology guidelines. All patients aged 50 years or younger who were admitted to the CUC with ACS and gave informed consent were included and followed until discharge or death. Among 98 ACS admissions of all ages, 31 (31.6%) concerned patients aged 50 years or younger, who represented 2.6% of the 1,197 admissions. Among the 31 patients included, the mean age was 40.9 ± 7.7 years, with a marked male predominance (87.1%). Pre-event cardiovascular risk, estimated descriptively with the SCORE2 charts, was low in 48.4% of patients. The mean time from symptom onset to admission was 37.8 ± 41.3 hours, and 58.1% of patients were admitted more than 12 hours after onset. ST-elevation ACS accounted for 71.0% of cases. A high probability of atherosclerotic origin according to an exploratory, non-validated score was found in 96.8% of patients; it could not be confirmed angiographically in most of them. All patients except the one who died received the BASIC regimen (beta-blockers, antiplatelet agents, statins, renin–angiotensin system inhibitors and control of cardiovascular risk factors). Thrombolysis was indicated in nine patients, performed in seven (22.6%) and successful in six. Five patients (16.1%) underwent coronary angiography, which showed significant stenoses in three of them; these three patients received drug-eluting stents. At least one in-hospital complication occurred in 41.9% of patients, and in-hospital mortality was 3.2%. In this single-center series, ACS in patients aged 50 years or younger accounted for about one third of ACS admissions. Most of the risk factors observed were modifiable. These descriptive findings, limited by the small sample and the lack of systematic coronary angiography, support the strengthening of preventive measures and of access to reperfusion.
VL  - 10
IS  - 4
ER  -
University Cardiology Clinic, National Teaching Hospital Hubert Koutoukou Maga of Cotonou, Cotonou, Benin
University Cardiology Clinic, National Teaching Hospital Hubert Koutoukou Maga of Cotonou, Cotonou, Benin
University Cardiology Clinic, National Teaching Hospital Hubert Koutoukou Maga of Cotonou, Cotonou, Benin
University Cardiology Clinic, National Teaching Hospital Hubert Koutoukou Maga of Cotonou, Cotonou, Benin
University Cardiology Clinic, National Teaching Hospital Hubert Koutoukou Maga of Cotonou, Cotonou, Benin
University Cardiology Clinic, National Teaching Hospital Hubert Koutoukou Maga of Cotonou, Cotonou, Benin
University Cardiology Clinic, National Teaching Hospital Hubert Koutoukou Maga of Cotonou, Cotonou, Benin
University Cardiology Clinic, National Teaching Hospital Hubert Koutoukou Maga of Cotonou, Cotonou, Benin
Cardiology Department, Calavi International Hospital, Abomey-Calavi, Benin

Information


 Share This Article
 Twitter
 Linked In
 Facebook

 Copy
 Download